Why Straining on the Toilet Undoes Weeks of Pelvic Floor Work
Quick Answer: Straining generates high, sustained downward pressure on the pelvic floor, and doing it daily can outweigh the strengthening effect of a consistent exercise routine. The three fixes that matter are a footstool to raise the knees above the hips, breathing out during the effort instead of holding the breath, and not sitting longer than about five minutes.
You can do everything right for eight weeks and see almost no change, because the exercise is being cancelled by two minutes of bearing down every morning.


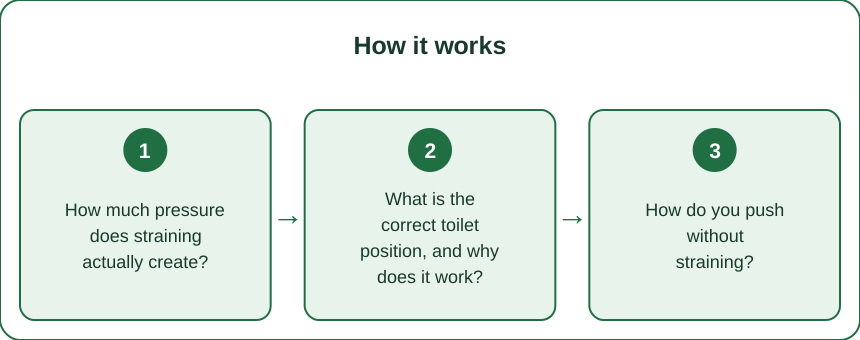
How much pressure does straining actually create?
Considerably more than most people assume, and critically it is sustained rather than momentary.
A cough or a sneeze creates a high pressure spike lasting a fraction of a second. Straining with a held breath creates a lower peak but holds it for many seconds, repeatedly. Connective tissue responds to load duration, not just magnitude, so a long moderate load can be more damaging than a brief large one.
The pelvic floor sits at the bottom of the abdominal cavity like the base of a pressurized canister. Anything that raises intra-abdominal pressure pushes down on it. During a Valsalva strain, the diaphragm is locked, the abdominal wall contracts, and there is only one direction for that pressure to go.
Do that for two minutes a day for a year and you have applied a load that no amount of pelvic floor exercise was designed to offset. This is why clinicians treating prolapse and incontinence often ask about bowel habits before they ask about exercise.
What is the correct toilet position, and why does it work?
Knees above hips, feet supported, lean forward slightly, and let the belly relax outward.
The anatomical reason is the puborectalis muscle. It slings around the rectum and pulls it forward, creating a bend called the anorectal angle. That bend exists to maintain continence when you are upright, and it needs to straighten for easy evacuation.
Sitting at conventional toilet height leaves the angle partially maintained, so you are pushing against your own continence mechanism. Raising the knees above the hips relaxes the puborectalis and opens the angle, which is the entire basis for the footstool.
A stool of 15-23 cm is typical, but the correct height is whatever puts your knees clearly above your hip crease. A stack of books works identically to a purpose-built product.
Leaning forward with forearms on thighs adds a small further improvement and, importantly, discourages the upright bracing posture that makes breath-holding feel natural.
How do you push without straining?
The technique has a name in pelvic health practice: brace and breathe out, sometimes taught as the “blow before you go.”
The sequence is: sit in the supported position, take a normal breath in and let the belly relax and widen, then breathe out through slightly pursed lips or make a low humming sound while gently widening the waist. Do not hold the breath. Do not clench the jaw. Do not go red in the face.
The pressure you generate this way is lower, more controlled, and directed more usefully. It also cannot be sustained past the length of an exhale, which builds a natural limit into the effort.
The cue that helps most people: think about widening rather than pushing down. The abdominal wall should move outward, not the pelvic floor downward. If you put a hand on your lower belly you should feel it expand.
If it does not work within a couple of gentle attempts, get up and come back later. That is a real instruction, not a consolation prize.

5 Habits That Are Quietly Loading Your Pelvic Floor
1. Sitting on the toilet with a phone. Time on the toilet is the strongest predictor of unnecessary straining, and the phone is the reason five minutes becomes fifteen. Sustained sitting with the pelvic floor unsupported and the rectum stretched is a load in itself.
2. Holding it. Repeatedly deferring the urge dries and hardens stool and desensitizes the signal, making the next attempt harder. The habit is understandable at work and expensive over years.
3. Breath-holding during lifting. The same Valsalva mechanism, applied in the gym. For most non-competitive lifting, exhaling on the effort is the safer default, especially in the first year postpartum or with existing symptoms.
4. Chronic cough left untreated. A persistent cough from allergies, reflux, or smoking applies thousands of pressure spikes over a season. Treating the cough is a pelvic floor intervention.
5. Dehydration paired with high fiber. Increasing fiber without increasing fluid is one of the more common ways people make constipation worse while believing they are fixing it. Fiber needs water to work.
The one that surprises people: the fix is almost never more kegels. If straining is the primary load, adding contractions to an already overworked and possibly over-tight floor can worsen symptoms. Reduce the load first, then train.
How long before the change shows up?
Faster than a strengthening program, which is part of what makes it worth doing first.
Posture and breathing changes affect the very next attempt. Most people notice reduced effort within a few days. The downstream symptoms, whether that is heaviness, leaking, or a dragging sensation, typically take two to six weeks to respond, because you are removing an ongoing insult rather than adding a stimulus.
If stool consistency is the underlying issue, addressing it takes longer and matters more. The practical targets are adequate fluid, fiber increased gradually rather than suddenly, movement most days, and a consistent time of day, since the bowel responds strongly to routine.
If symptoms do not improve in six weeks with consistent changes, that is the point to see a pelvic health physiotherapist rather than to try harder. Persistent difficulty can involve a coordination problem where the pelvic floor contracts instead of relaxing during attempts, and that specifically requires guided retraining rather than self-management.
This is general information, not medical advice. Blood, sudden changes in bowel habit, unexplained weight loss, or pain warrant prompt medical assessment.
FAQ: Straining and Pelvic Floor Questions, Answered
Do I need to buy a special stool?
No. Any stable object that raises your knees above your hips does the job identically. The mechanism is the joint angle, not the product.
Is straining bad even if I have no symptoms?
It is a load whether or not it has produced symptoms yet, and pelvic floor problems typically accumulate over years before they announce themselves. The cost of changing the habit is close to zero, which makes it worth doing prophylactically.
Should I stop doing kegels while I fix this?
Not necessarily, but check whether you can fully relax between contractions. If you cannot, or if you have pain, urgency, or difficulty starting a stream, prioritize relaxation and breathing work and get assessed before adding more strengthening.
TL;DR:
- Straining applies sustained downward pressure that can outweigh a whole exercise program
- Knees above hips relaxes the puborectalis and opens the anorectal angle
- Breathe out during the effort and widen the waist rather than pushing down
- Cap toilet time at about five minutes and leave the phone outside
Before you add another set of kegels, put a stool under your feet and stop holding your breath. That is the higher-leverage change, and it works this week.
Keep Reading
This article is for general informational purposes only and is not medical advice. Always consult a qualified health professional for guidance specific to you.
